
Thyroid & Parathyroid Tumors
Meticulous thyroidectomy and parathyroidectomy preserving the recurrent laryngeal vocal nerves and parathyroid glands while removing malignant endocrine nodules.
Overview & Surgical Philosophy
Surgical removal of thyroid and parathyroid lesions requires microscopic dissection along the trachea to preserve vocal cord nerve function and avoid hypocalcemia, while ensuring complete eradication of primary tumor and central neck nodes.
Common Symptoms & Clinical Signs
A palpable nodule or swelling in the lower front of the neck, hoarseness of voice, difficulty swallowing or feeling of fullness in the throat, swollen neck nodes.
Early presentation significantly increases the likelihood of conservative, organ-sparing surgical interventions.
Diagnostic Workup & Staging
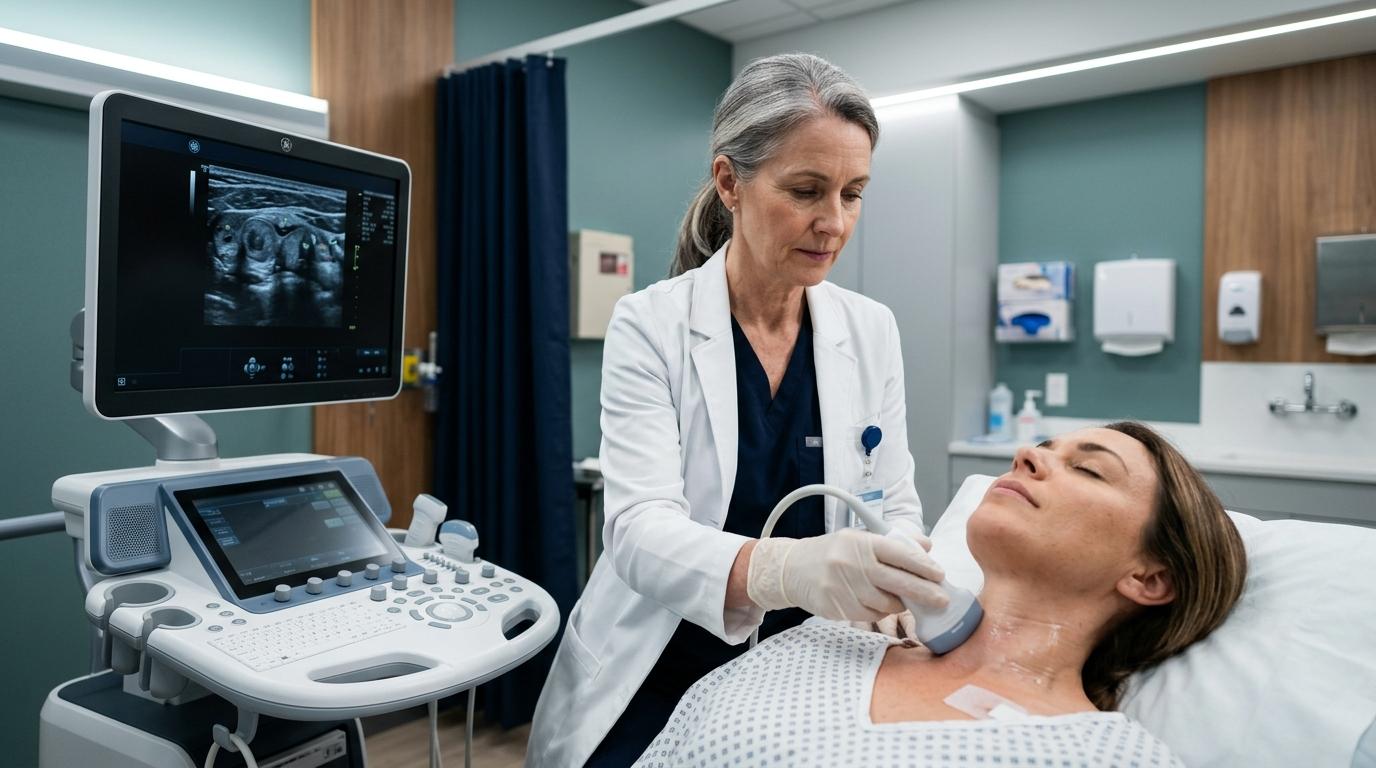
High-resolution neck ultrasound with TI-RADS scoring, Ultrasound-guided FNAC (Bethesda classification), Serum TSH, Free T3/T4, Calcium, and PTH levels.
Surgical Approaches & Techniques
Hemithyroidectomy, Total Thyroidectomy with central compartment neck dissection, Selective lateral neck dissection for nodal metastasis, Minimally invasive parathyroidectomy.
Post-Operative Care & Follow-Up
Serum calcium monitoring, vocal cord mobility assessment, thyroid hormone replacement calibration, and radioactive iodine (RAI) therapy coordination when indicated.

Lt Col (Dr) Rahul Sandhu
Surgical Oncologist
15+ years experience in clinical cancer surgery & military trauma care.
Other Cancer Specialities
Discuss Your Case Directly with Dr. Rahul Sandhu
Personalized oncological assessment and second opinions in Mohali & Kharar.